Aetheris
The practice management and electronic health record system, configured for your specialty rather than for everyone's.
 Practice software
What it is
One system covering the diary, the patient record with the full consultation structure, an ambient scribe, prescribing, documents, a video clinic, laboratory ordering, insurers, billing, a patient portal, an inbox, tasks and marketing. Choose the specialty once and the clinical module, consultation template, pathways, formulary and letter set all change with it.
Why it matters
A general system serves nobody in particular. The fields a fertility clinic must capture are not the fields a dentist must capture, and a form long enough to hold both is a form nobody completes. Ten specialties are configured out of the box, each with the records that specialty is actually required to keep.
Safety in the endpoint, not the button
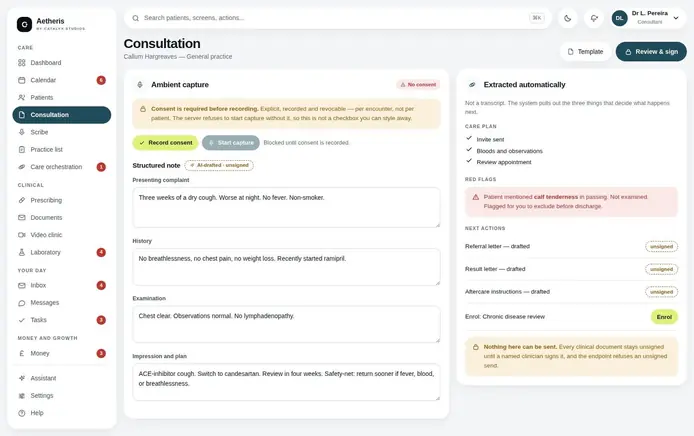
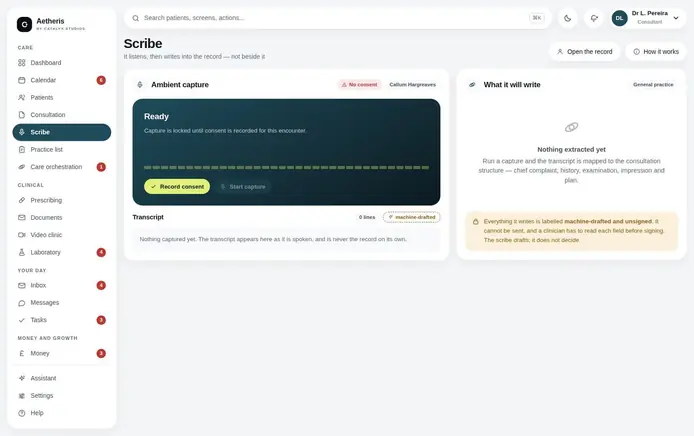
A rule enforced by hiding a menu item is not a rule. Recording is blocked without consent for that encounter. Allergies are checked at the moment of signature. A repeat is blocked while monitoring is overdue. Nothing clinical can be sent unsigned. Each of those lives where the call is made, so re-enabling a control in a browser console changes nothing.
Everything closes its loop
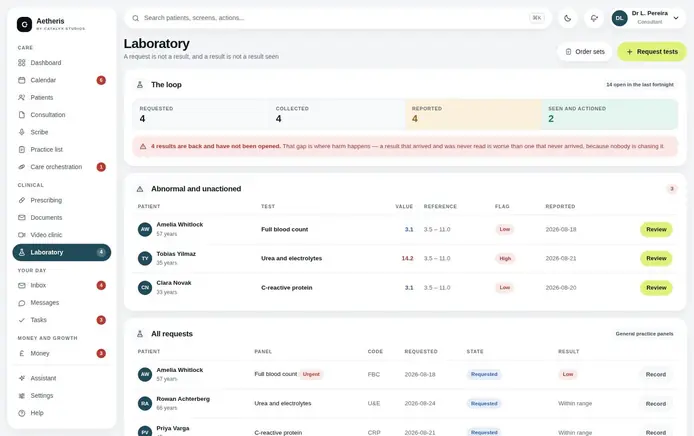
Referred is not seen. Sent is not signed. A specimen sent is not a result read. Each stays open until it is genuinely finished, which is the difference between a system that reports and one that helps.
Included, every time.
- Ten specialties configured out of the box
- 97-field structured consultation record
- Ambient scribe that writes into the record
- E-prescribing with allergy checks at signature
- Laboratory ordering with a four-state loop
- Insurer contracts, claims and appeals
- Billing ledger, aged debt and payment plans
- Patient portal on your own domain
- Video clinic with consent-gated recording
- Multiple locations and external calendars
- Migration in, and an open export out
Said plainly.
The things a supplier normally leaves you to discover.
- It does not diagnose, treat or make clinical decisions.
- It is not a UKCA-marked medical device.
- It will not send anything clinical that has not been signed.
Real screens, not a mock-up.



What this changes in a private practice.
The whole practice in one place
Records, diary, letters, prescribing, billing, insurers and the patient portal, so nobody is re-typing the same appointment into a third system.
Configured to your specialty
The consultation template, the pathways, the formulary and the letters change entirely between a dentist, a psychiatrist and a fertility clinic. So does the software.
Time back in every clinic
The note written while you consult, the letter drafted from the note, the recall set automatically. Minutes each, several times a day.
Modern private practice
Practices are consolidating. Five subscriptions that do not talk to each other cost more in reconciliation than they ever saved in licence fees, and every gap between them is somewhere a result or a payment goes missing. The direction of travel is one record, many views.
Useful, and bounded
The ambient scribe is the clearest case for AI in a consulting room: it listens, drafts the note into the right fields, and leaves you editing rather than typing. It drafts and never files. Nothing enters the record until a clinician has read it, and the audit log shows who released what.
Ten specialties. Ten different systems.
Choosing the specialty changes the clinical module, the consultation template, the pathways, the formulary, the letters and the numbers on the dashboard. These are the features each one gains that the others do not need.
 General practice
Undifferentiated problems, long relationships and everything that must not be missed
One active problem list per patient, ranked and dated. In general practice the record IS the continuity, because the next contact is often with somebody else.
What the patient was told to look out for, and by when to come back. If it is not written down, it was not said.
Diabetes, hypertension, asthma and the rest carry review cycles. The system holds the cycle and invites; the clinician decides.
Weight loss, haemoptysis, new headache over fifty. Flagged from what was recorded, never diagnosed.
A repeat with no review date is an indefinite prescription. Each one carries a stop date and a reason.
Referred is not seen, and seen is not reported. The referral stays open until the letter is back and read.
 Dentistry
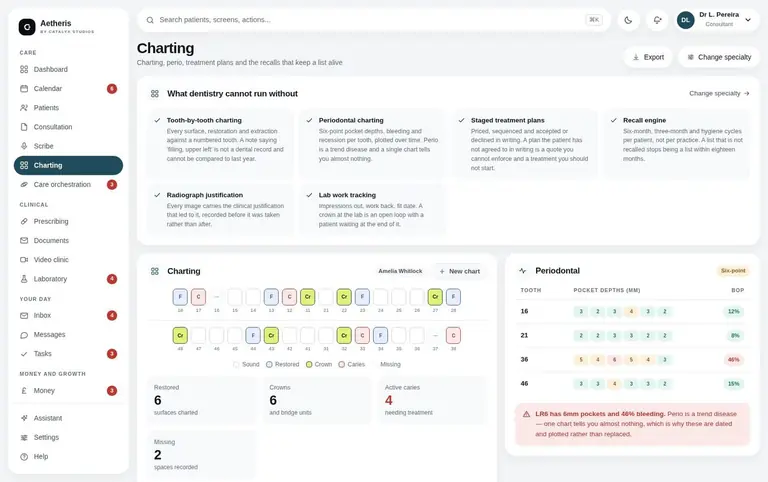
Charting, perio, treatment plans and the recalls that keep a list alive
Every surface, restoration and extraction against a numbered tooth. A note saying 'filling, upper left' is not a dental record and cannot be compared to last year.
Six-point pocket depths, bleeding and recession per tooth, plotted over time. Perio is a trend disease and a single chart tells you almost nothing.
Priced, sequenced and accepted or declined in writing. A plan the patient has not agreed to in writing is a quote you cannot enforce and a treatment you should not start.
Six-month, three-month and hygiene cycles per patient, not per practice. A list that is not recalled stops being a list within eighteen months.
Every image carries the clinical justification that led to it, recorded before it was taken rather than after.
Impressions out, work back, fit date. A crown at the lab is an open loop with a patient waiting at the end of it.
 IVF & fertility
Cycles, embryology and the consents that govern both
Stimulation day, follicle counts and hormone levels on one timeline, so a dose change is made against the trend and not against the last reading.
Every fertilisation, grade and transfer with the second witness named. Witnessing that is not recorded did not happen.
Gametes and embryos carry a statutory storage clock. The system counts down and warns before consent lapses, not after.
A cycle has two patients. Results, consents and funding attach to the couple, not to one chart with the other in free text.
Which cycle of the funded allocation this is, and what happens when it runs out.
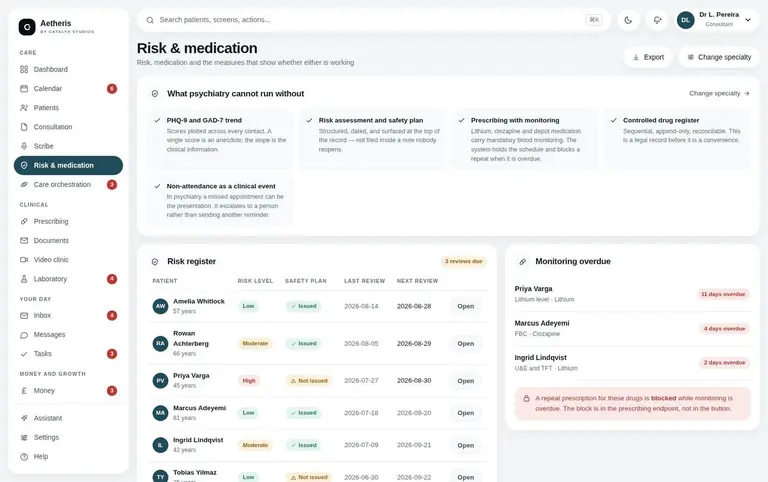 Psychiatry
Risk, medication and the measures that show whether either is working
Scores plotted across every contact. A single score is an anecdote; the slope is the clinical information.
Structured, dated, and surfaced at the top of the record — not filed inside a note nobody reopens.
Lithium, clozapine and depot medication carry mandatory blood monitoring. The system holds the schedule and blocks a repeat when it is overdue.
Sequential, append-only, reconcilable. This is a legal record before it is a convenience.
In psychiatry a missed appointment can be the presentation. It escalates to a person rather than sending another reminder.
 Psychology
Sessions, measures and the point at which therapy has done its work
Therapy is sold and delivered in blocks. Sessions used, remaining and expiring, visible to the therapist and the front desk.
CORE-10 or PHQ-9 captured every session, plotted against the reliable-change threshold rather than eyeballed.
The formulation is the treatment plan. It is a first-class field, versioned, not a paragraph in the first note.
Issued, and marked done or not done by the patient before the next session.
Which cases were taken to supervision and when — a professional requirement, not an optional extra.
 Surgery
Lists, consent, implants and what happened at thirty days
The list, the order, the kit, and the checklist signed off for each case.
Consent taken at the decision and confirmed on the day, with the cooling-off period recorded between them.
ASA grade, fitness, anticoagulation, and anything that would stop the case — resolved before the day, not on it.
Every implant with its lot number and the patient it went into. When a batch is recalled you need the list in seconds.
A specimen sent is not a specimen resulted. Open until the report is back and seen.
Complications and readmissions recorded against the operating surgeon, because that is the only version of the number that improves anything.
 Dermatology
Lesions mapped, imaged, biopsied and followed to a result
Every lesion sited on a body map with a stable identifier, so the mole discussed today is provably the one imaged last year.
Sequential images per lesion, compared side by side. Change over time is the diagnosis.
Open from the moment the specimen leaves until the report has been seen and acted on.
A two-week-wait referral starts a timer that the system owns, and escalates before the breach, not after.
Cumulative dose, bloods and review dates held against the treatment, not the calendar.
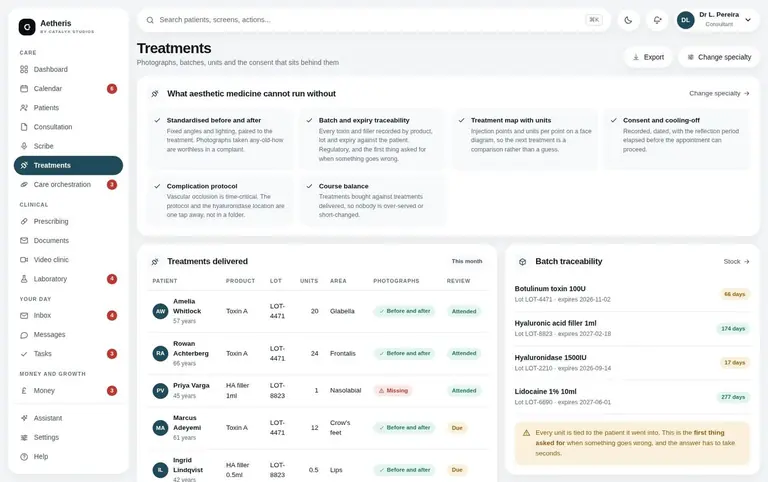 Aesthetic medicine
Photographs, batches, units and the consent that sits behind them
Fixed angles and lighting, paired to the treatment. Photographs taken any-old-how are worthless in a complaint.
Every toxin and filler recorded by product, lot and expiry against the patient. Regulatory, and the first thing asked for when something goes wrong.
Injection points and units per point on a face diagram, so the next treatment is a comparison rather than a guess.
Recorded, dated, with the reflection period elapsed before the appointment can proceed.
Vascular occlusion is time-critical. The protocol and the hyaluronidase location are one tap away, not in a folder.
Treatments bought against treatments delivered, so nobody is over-served or short-changed.
 Sports medicine
Injury, measurement and a defensible return-to-play decision
Mechanism, date, tissue and side. Recurrence is the outcome that matters and you cannot see it without this.
Range, strength and hop-test symmetry, captured as numbers over time rather than as 'improving'.
Explicit criteria per stage with a named clearance. The decision is a record, not a conversation.
Requested, performed, reported, seen — the same four states as any other loop that can be dropped.
For club and team work: who is available, who is modified, who is out, without naming a diagnosis to a coach.
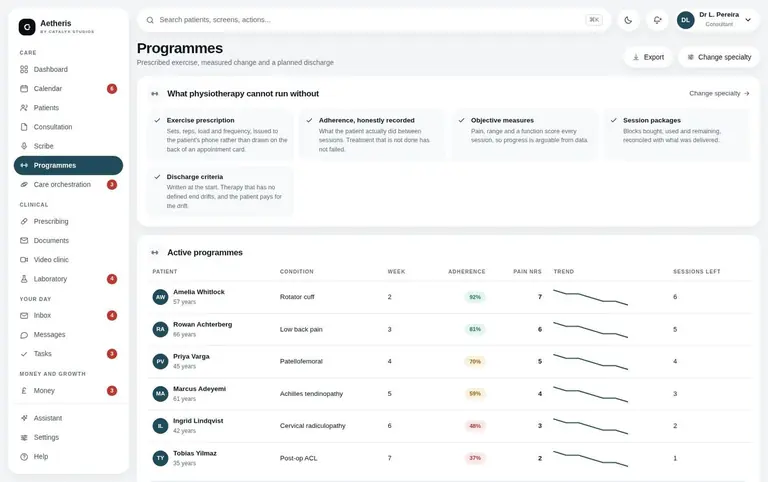 Physiotherapy
Prescribed exercise, measured change and a planned discharge
Sets, reps, load and frequency, issued to the patient's phone rather than drawn on the back of an appointment card.
What the patient actually did between sessions. Treatment that is not done has not failed.
Pain, range and a function score every session, so progress is arguable from data.
Blocks bought, used and remaining, reconciled with what was delivered.
Written at the start. Therapy that has no defined end drifts, and the patient pays for the drift.
Talk to a clinician about it.
Thirty minutes on video, no charge, and we will tell you honestly if we are not the right studio for it.